
A75-year-old male presented with symptomatic severe aortic stenosis (valve area 0.8 cm2, mean gradient 42 mmHg) and mild regurgitation. Left ventricular (LV) function was normal. Computed tomography showed a tricuspid, heavily calcified aortic valve (particularly the non-coronary cusp), an annulus area of 497 mm2, a sinus of Valsalva diameter of 32 mm, a sinotubular junction (STJ) height of 21 mm, an STJ width of 30 mm, a low left coronary height of 7.7 mm, and a thickened, long (15.7 mm) left coronary cusp (LCC) (Figure 1A). The Heart Team consensus was that he was at intermediate surgical risk due to obesity and chronic kidney disease, and both surgery and transcatheter aortic valve implantation (TAVI) were viable treatment options. The patient subsequently declined surgery.
TAVI with bioprosthetic aortic scallop intentional laceration to prevent iatrogenic coronary artery obstruction (BASILICA)1 was planned to minimise the risk of left coronary occlusion and to preserve future coronary access. A balloon-expandable transcatheter heart valve (THV) was chosen over a self-expanding one, as it would allow more options for future THV-in-THV, and to minimise the risk of permanent pacemaker requirement as his membranous septum length was short at 1.2 mm. Through an 8 Fr Amplatz left (AL) 2 guide catheter, an Astato XS 20 wire (Asahi Intecc) loaded within a PiggyBack (Teleflex) microcatheter was positioned at the root of the LCC. Coronary protection was also performed as a backup measure, a Judkins left 4 guide catheter (Figure 1B – white arrows) was placed in the left coronary ostium, and a Runthrough wire (Terumo) (Figure 1B – black arrow) was advanced into the left anterior descending artery. The AL2 guide catheter and Astato wire were visualised on transoesophageal echocardiography (TOE) to be directly below the left main ostium; as the trajectory appeared satisfactory on contrast angiography, the wire was electrified and advanced. However, the wire advanced laterally (Figure 1C, Figure 1D). Wire advancement was immediately stopped and retracted. A root aortogram showed mild myocardial staining that remained stable (Figure 1E). After making a 45° bend at the distal tip, the Astato wire was electrified and advanced into the left ventricular outflow tract (LVOT) (Figure 1F, Figure 1G). Leaflet laceration was performed and confirmed with TOE. A 26 mm SAPIEN 3 Ultra valve (Edwards Lifesciences) was then implanted without predilatation. Shortly after, hypotension occurred. TOE showed a pericardial tamponade, and root aortography showed contrast extravasation into the pericardial space (Figure 1H). Immediate pericardiocentesis was performed, extracorporeal membrane oxygenation (ECMO) support was initiated, and open surgical repair was undertaken. A perforation originating at the base of the LCC, extending through the annulus and into the LV myocardium, was identified (Figure 1I) and repaired. Valve replacement was performed, and the ECMO was discontinued 1 week later. This case illustrates two important lessons. First, it is critical to ensure that the Astato wire is directed back towards the centre of the LVOT before advancement. A smaller catheter, such as a Judkins right (JR) 4 catheter, to facilitate wire navigation was not used in this case as the trajectory accorded by the oversized AL2 guide catheter appeared satisfactory. With the benefit of hindsight, the guide catheter and wire trajectory were suboptimal. Although there have been many cases where BASILICA has been performed successfully with an oversized AL guide catheter and Astato wire loaded within a microcatheter, the authors now perform all such procedures using a smaller, long-shaft, curved catheter (e.g., JR4, MP, pigtail) within the larger AL guide catheter to ensure a correct wire trajectory and improve procedural success. Second, if wire injury occurs to the annulus or myocardium, the procedure must not continue until the injury has completely healed. A 0.014 inch wire injury may be benign; conversely, valve implantation following a wire injury can result in severe complications.
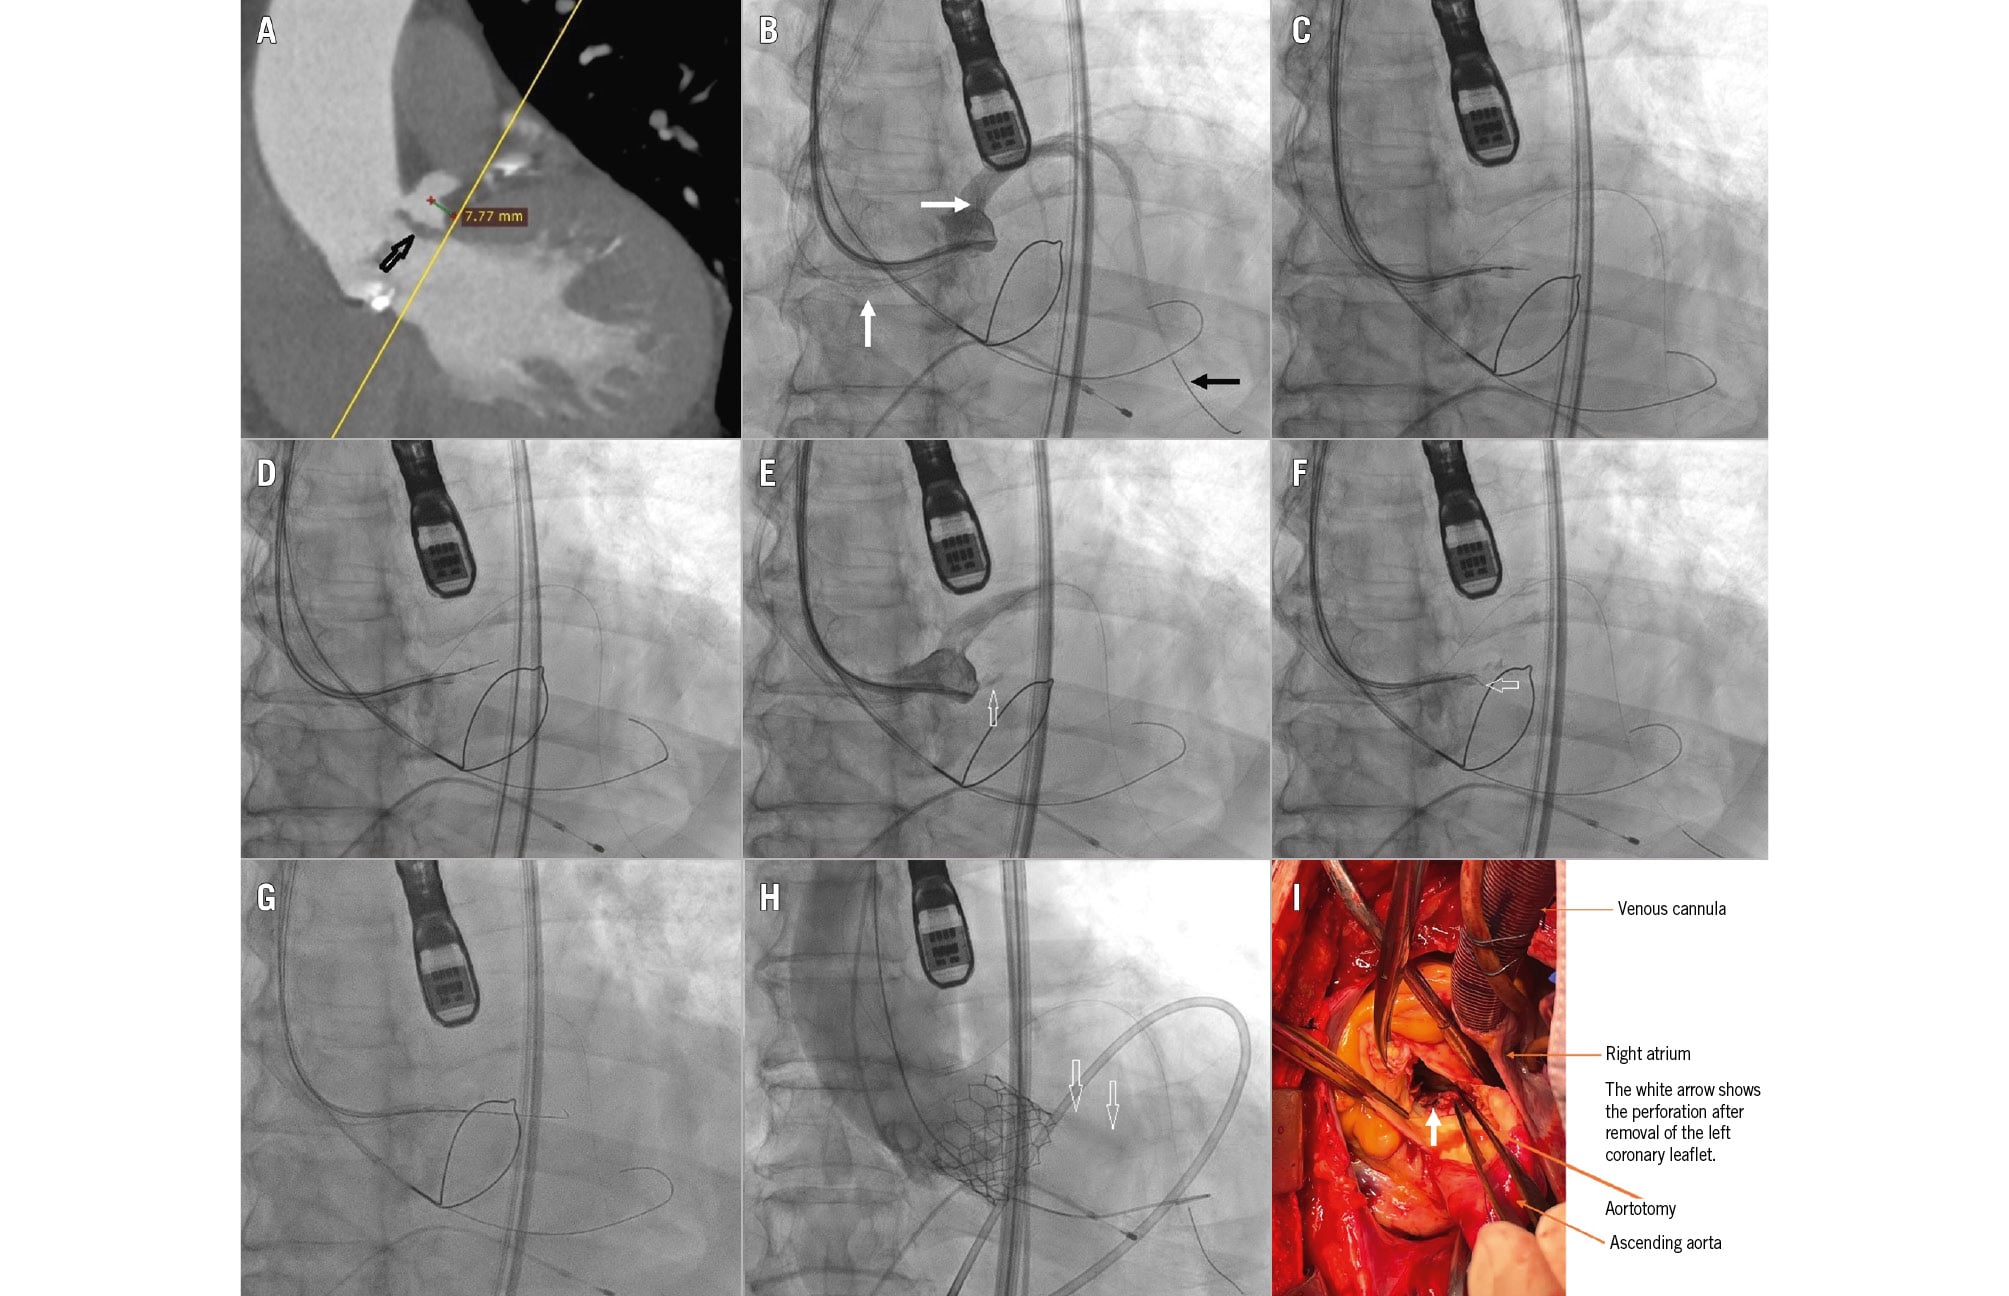
Figure 1. CT assessment, TAVI procedure, and surgical findings. A) CT showing low left coronary height (7.7 mm); long and thickened LCC leaflet (black arrow). B, C, D) Fluoroscopy showing the AL2 guide catheter and Astato wire at the base of the LCC, the JL4 guide catheter (white arrows) at the left coronary ostium, the Runthrough wire in the LAD (black arrow), and wire traversal in a lateral direction. E) Contrast fluoroscopy showing mild staining (arrow) of the LV myocardium. F, G) Fluoroscopy showing the Astato wire tip with a 45° bend (arrow) at the base of the LCC, and wire traversal into the LVOT. H) Contrast fluoroscopy showing extravasation (arrows) into the pericardial space. I) View after the calcified aortic leaflets have been removed, showing the perforation originating at the base of the LCC, extending through the annulus and into the LV myocardium. AL: Amplatz left; CT: computed tomography; JL: Judkins left; LAD: left anterior descending artery; LCC: left coronary cusp; LV: left ventricular; LVOT: left ventricular outflow tract
Conflict of interest statement
P.T.L. Chiam is a proctor for Edwards Lifesciences. The other authors have no conflicts of interest to declare.
